

PCOD and PCOS are not two different conditions. Polycystic ovary syndrome (PCOS) is the recognised diagnosis. PCOD is a loose Indian term that appears in no international guideline, has no diagnostic criteria of its own, and does not describe a separate, milder disease. PCOS itself is a hormonal and metabolic condition that changes how the ovaries release eggs, and it is diagnosed on a combination of features rather than on a scan alone. This page explains what your report means and how the diagnosis is properly made.
No, but not for the reason most articles give.
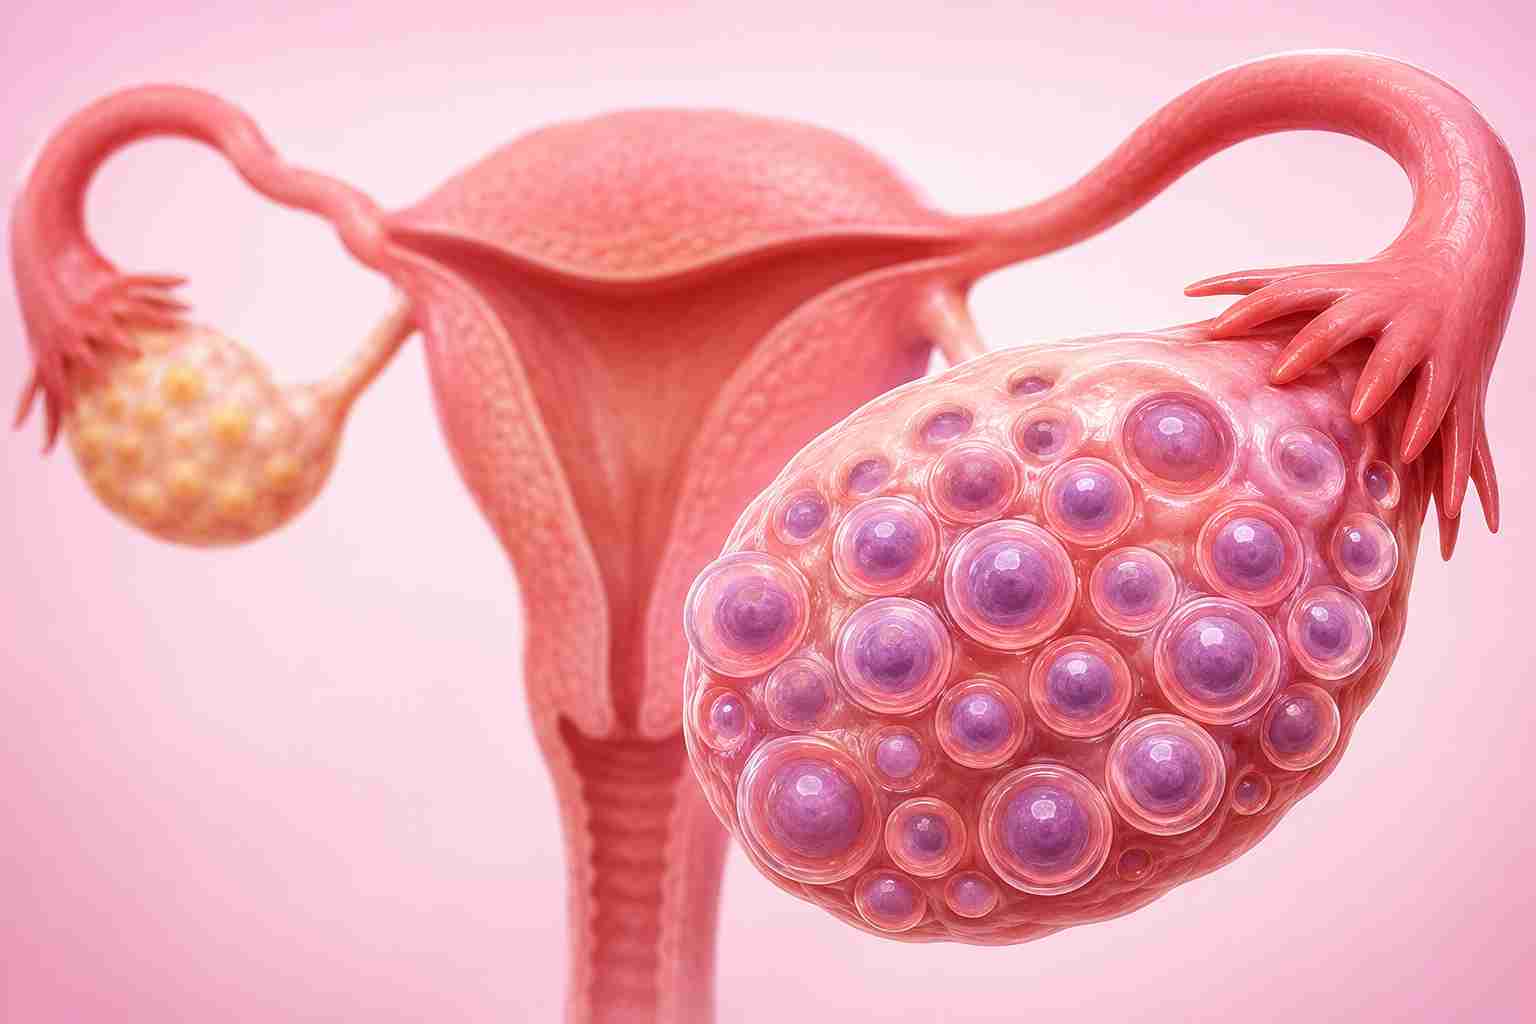
PCOD is not a milder version of PCOS. It is not a diagnosis at all. There are no PCOD criteria, no PCOD test and no PCOD treatment pathway, because there is no such diagnostic entity. The 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome, developed with the American Society for Reproductive Medicine, the Endocrine Society, the European Society of Endocrinology and the European Society of Human Reproduction and Embryology, recognises polycystic ovary syndrome as the condition, and polycystic ovarian morphology (the appearance of many small follicles on an ultrasound scan) as a finding. Neither of those is called PCOD.
One specific claim circulates very widely on Indian health pages, and now in AI-generated summaries: that PCOD is a condition in which the ovaries release immature eggs, that PCOS is the one that involves male hormones, and that PCOD is the milder, lifestyle-triggered, reversible version. That distinction has no guideline basis anywhere. It is not a simplification of the evidence. It is a description of two conditions, only one of which exists.
So what does it mean when a report or a clinician says PCOD? Almost always one of two things. Either the ovaries showed polycystic ovarian morphology on a scan, which is a description and not a diagnosis, or the woman does have polycystic ovary syndrome and the older word is being used out of habit. Those two situations call for very different responses, which is precisely why the word matters.
If you have been told you have PCOD, the useful question is not whether it is better or worse than PCOS. It is whether you meet the criteria for PCOS, and nobody can answer that from a scan alone.
PCOS is a hormonal and metabolic condition that affects ovulation, the release of a mature egg from the ovary. In PCOS, follicles (the small fluid-filled sacs in which eggs develop) begin to grow but frequently do not mature and release. Cycles become irregular or stop altogether, and androgen levels (hormones such as testosterone, present in every woman but higher in PCOS) rise, affecting skin and hair.
The name is a problem, and it is worth naming the problem directly. The cysts in polycystic ovaries are not cysts. They are follicles that have not matured and released, sitting at 2 to 9 mm across, often around the edge of the ovary. They are not the large ovarian cysts that require monitoring or surgery. They do not need to be drained, and they do not rupture. Much of the fear attached to this condition comes from a poorly chosen word.
The 2023 guideline group formally endorsed an earlier international recommendation that the name of the condition is a distraction and should be changed, and work towards a new name is under way. Until that happens, polycystic ovary syndrome remains the term you will see on reports and in clinics.
Doctors diagnose PCOS when at least two of three features are present, and other causes have been excluded. No single test confirms it.
These are the Rotterdam criteria, updated in 2023 from consensus-based to evidence-based. The key 2023 change is that AMH may now replace an ultrasound scan in adults. Only one is needed, and doing both is actively discouraged because it increases the risk of overdiagnosis.
A second point spares many women an unnecessary scan. Where irregular cycles and raised androgens are both present, the diagnosis is already established. Neither an ultrasound nor an AMH test is required.
Excluding other causes is not optional. Thyroid disease, a raised prolactin level, and non-classic congenital adrenal hyperplasia can each produce a similar picture, and they are checked before PCOS is confirmed.
And the honest answer to the question that brings most people here: no single blood test confirms PCOS. AMH in particular should not be used on its own to make the diagnosis. The diagnosis is a combination of features, not a result on a page. For a fuller walk-through of the tests used to assess PCOS, including what happens at each step, see the detection guide.
It describes what the ovaries looked like. It is not a diagnosis.
When a scan report says both ovaries show polycystic morphology, the radiologist is recording that each ovary contained a larger-than-usual number of small follicles, often arranged around the edge, sometimes described as a string-of-pearls appearance. That is an observation about appearance. It is one of the three PCOS features, and one feature is not a diagnosis. You will also see it abbreviated as PCOM.
These report wordings all describe the same finding:
Bulky is a size descriptor, not a severity grade. It means the ovary measured larger than average, usually 10 ml or more in volume. It does not mean the condition is advanced, and it does not mean that something is about to go wrong.
Mild and early are not clinical grades either. There is no staging system for polycystic ovarian morphology, and there is certainly no mild PCOD, because PCOD is not a diagnosis that could be graded in the first place.
Polycystic ovarian morphology on its own, without raised androgens and without ovulatory dysfunction, does not meet the criteria for PCOS. It is found in women with entirely regular cycles and no symptoms, and in that situation it usually needs no treatment at all. What it does justify is a proper conversation about your cycles and any skin or hair changes, because the answer lies there, not in the scan.
Symptoms vary widely between women, and a woman can meet the diagnostic criteria with very few visible signs.
Two things are worth saying plainly here. Symptoms do not begin because of weight gain, although weight change can make them more noticeable. And the absence of visible signs does not rule PCOS out: a woman of any body size, including a slim woman with clear skin, can meet the criteria.
The cause is not fully established. What is well supported is that insulin resistance (a reduced response to insulin, so the body produces more of it) and genetic factors play a central role. Higher insulin levels drive the ovary to produce more androgens, which in turn interfere with the maturation and release of follicles. Family clustering is common, and male relatives of women with PCOS have a higher rate of metabolic problems, which points the same way.
PCOS is not caused by a woman’s diet or lifestyle choices alone, and framing it that way is both inaccurate and unhelpful. The evidence does not show consistent lifestyle or behavioural differences between women with PCOS and women without it. Weight gain can worsen PCOS features, and weight management can improve them considerably. That is not the same as causing the condition, and the distinction matters, because women with PCOS report a great deal of blame in healthcare settings that the evidence does not support.

A teenager should not be diagnosed with PCOS on a scan.
In adolescents, both raised androgens and ovulatory dysfunction are required for a diagnosis. Two of three is not enough at this age, and the third criterion is set aside entirely: ultrasound and AMH are not recommended for diagnosis in adolescents, because they lack specificity. Irregular cycles, acne and multiple small follicles are common and often entirely normal in the years after menarche (the first period).
Scan-based assessment of ovarian morphology is not recommended until eight years after the first period. Before that point, a scan showing many follicles is describing a normally developing ovary at least as often as it is describing anything else. Irregular cycles are also expected in the first year after menarche, and the definition of what counts as irregular loosens further the closer a girl is to her first period.
Where a teenager has the typical features but does not meet the full criteria, the guideline recommends recording her as at increased risk, with reassessment later rather than a diagnosis now. That is the correct answer, and it protects against a label that would follow her for life on insufficient evidence.
There is no cure for PCOS. Treatment is symptom-directed and goal-directed, and the right treatment depends entirely on what you want to address. All medication is prescriber-led and chosen in discussion with your clinician.
Combined hormonal contraception is the first-line medical option for irregular cycles, and it also protects the womb lining during long gaps between periods. If it is unsuitable or not tolerated, insulin-sensitising medication is an alternative for cycle regulation, and progestogen-only treatment can protect the lining.
Combined hormonal contraception is again first-line for excess hair growth. Laser and light-based hair reduction has good evidence behind it and also improves mood and quality of life, though women with PCOS often need more sessions than others. Anti-androgen medication has a limited role and is reserved for cases where at least six months of other treatment has not worked. It always requires reliable contraception alongside it.
Healthy eating and physical activity are the foundation, and no evidence shows that any one diet composition outperforms another. Insulin-sensitising medication is recommended primarily for metabolic features. Inositol supplements offer limited clinical benefit and are less effective than insulin-sensitising medication for the outcomes measured.
Ovulation induction medication is the usual starting point and works well for most women with PCOS, with further options available if it does not. That pathway is set out separately.
No medication, supplement or diet makes PCOS go away, and nothing on the market cures it. Treatment manages the features that matter to you.
The tests used to assess PCOS are individually inexpensive, and most women need only two or three of them rather than the full list. The ranges below are indicative and were supplied by Cloudnine Fertility rather than taken from an audited price list, so confirm current pricing with your centre.
The main cost driver is how many tests are genuinely needed. When irregular cycles and raised androgens are both present, no scan and no AMH test are required, removing the two largest items on the list. Only one of the scan or the AMH test is ever needed, never both. Once a diagnosis is established, ongoing costs are periodic metabolic checks rather than repeat diagnostic testing. Charges vary by city and by centre, and a consultation fee usually sits on top of the test costs.
PCOS does not mean you cannot get pregnant. It is one of the most common causes of difficulty conceiving, and one of the most treatable, largely because the underlying problem is ovulation, which can usually be restored. The guideline is explicit that women with PCOS should be reassured about their general reproductive potential and family size, while acknowledging that some will need medical assistance.
Claims that the chances of conceiving with PCOS are minimal or close to zero appear on live Indian health pages and are simply wrong. For how conception with PCOS is actually managed, from first-line treatment through to assisted options, see PCOS and fertility treatment in India.
PCOS is currently considered a lifelong condition, and it carries health implications well beyond fertility. Regardless of age or body size, women with PCOS have a higher risk of impaired glucose tolerance and type 2 diabetes, so glucose status should be checked at diagnosis and reassessed every one to three years. Cardiovascular risk is higher too, and the guideline recommends assessing every woman with PCOS for cardiovascular risk factors, with a lipid profile at diagnosis and blood pressure measured annually.
Obstructive sleep apnoea (repeated pauses in breathing during sleep) is significantly more common in PCOS independently of body size, and is worth raising if you snore and wake unrefreshed. Long gaps without periods leave the endometrium (the lining of the womb) unshed for extended stretches, which raises the risk of endometrial thickening and, less commonly, endometrial cancer. However, the absolute risk stays low and routine screening is not recommended. Cycle regulation is the main protection here.
Depression and anxiety are markedly more common in PCOS, and screening for both is recommended for every woman and adolescent with the condition. None of this is a reason for alarm. It is a reason for a small number of regular checks that are easy to keep up with once in place.
A scan report is not a diagnosis, and it is not a treatment plan. If you have been handed one and told you have PCOD, take it to a gynaecologist and ask whether you meet the criteria for polycystic ovary syndrome, rather than acting on the report alone.


