Ovarian Cysts and Fertility: Do They Affect Getting Pregnant?
October 25, 2026
Cloudnine
No items found.
Ovarian Cysts and Fertility: Do They Affect Getting Pregnant?
October 25, 2026
Cloudnine
No items found.
Most ovarian cysts do not affect your chance of getting pregnant. Finding one on a scan is usually not why a pregnancy hasn't happened yet. The majority are functional cysts, which form as part of a normal ovulation cycle and disappear on their own within a few cycles.
Two situations change the answer. An endometrioma, a cyst linked to endometriosis, can affect both egg reserve and the surrounding pelvic anatomy. And a cyst that is large, persistent, or recurring may need attention for reasons of its own.
Everything below is about telling those two apart from the far more common harmless finding.
Which ovarian cysts affect fertility and which do not
The table below covers the cyst types seen most often on a pelvic scan and what each usually means if you are trying to conceive. Type matters considerably more than size.
Cyst Type
Does It Affect Fertility?
What It Usually Means for You
Functional Cyst (Follicular)
No, in almost all cases.
Forms when a follicle continues growing instead of releasing its egg. It usually resolves on its own, often within two to three cycles.
Corpus Luteum Cyst
No.
Forms after an egg has been released. Its presence can indicate that ovulation has occurred.
Dermoid Cyst
Usually not.
Usually benign and slow-growing. It becomes more relevant if it grows large enough to affect the ovary or if removal is being considered.
Cystadenoma
Usually not.
A generally benign growth arising from the ovarian surface. It does not usually interfere directly with ovulation.
Paraovarian Cyst
Usually not.
Sits beside the ovary rather than within it, so the ovarian tissue and egg reserve are generally unaffected.
Endometrioma (Chocolate Cyst)
Yes, it can.
Associated with endometriosis. It can reduce ovarian reserve and may alter the position of the ovary or fallopian tube.
Large, Persistent, or Recurrent Cyst
Sometimes.
This describes a pattern rather than one specific cyst type. Persistence, growth, symptoms, and the underlying diagnosis are more important than size alone when assessing fertility.
What an ovarian cyst actually is
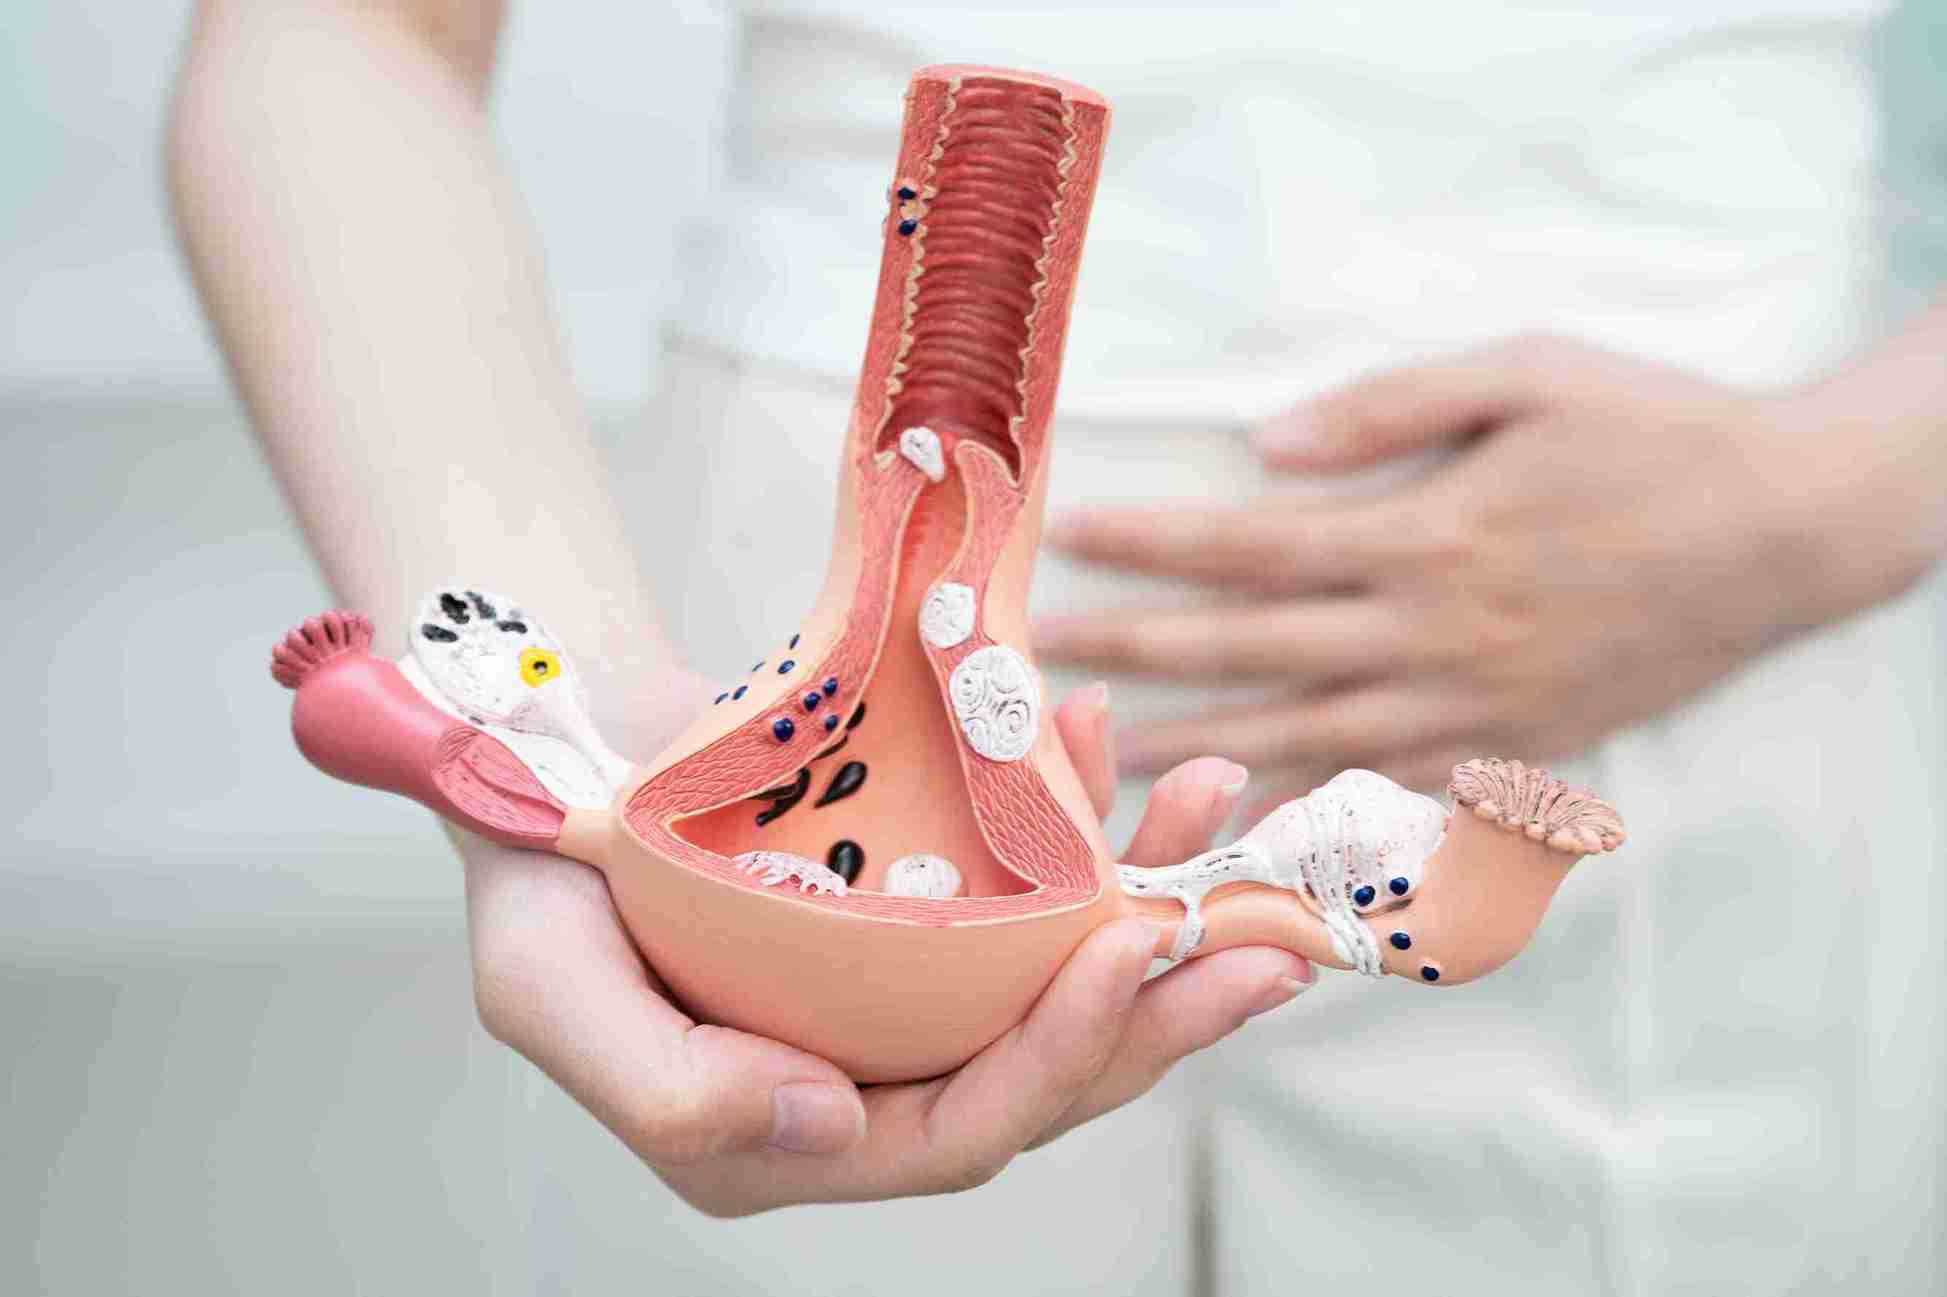
An ovarian cyst is a fluid-filled sac that forms in or on an ovary. Most are a by-product of the ovulation cycle rather than a disease. Each month, an ovary grows a follicle, a small fluid-filled sac that holds an egg. If that follicle releases the egg, the structure left behind becomes the corpus luteum, the temporary hormone-producing body that supports the second half of the cycle. If either of these keeps filling with fluid instead of shrinking away, what shows on a scan is a functional cyst.
That is why an ovarian cyst is one of the most common incidental findings on a pelvic ultrasound. Having had one at some point during your reproductive years is more common than abnormal, and most resolve without treatment within two to three cycles.
Clinically, what matters is not the presence of a cyst. It is the type, whether it has changed between scans, and whether it affects your reproductive function at all.
The cyst types that do not affect fertility
Functional cysts. These form as a direct result of the ovulation cycle. A follicular cyst is a follicle that carries on growing instead of releasing its egg. It does not damage ovarian tissue, and the ovary continues cycling normally once it resolves.
Corpus luteum cysts. This one is worth stating plainly. A corpus luteum cyst is evidence that ovulation happened, because the corpus luteum only exists after an egg has been released. When found in early pregnancy, it produces the hormone that supports the pregnancy through its first weeks. It is a sign that things are working, not a problem to be solved.
Dermoid cysts. These are benign growths containing ordinary body tissue such as skin or hair. They are usually present from birth and grow slowly. They do not affect hormone production or egg supply. They become relevant to fertility only if they grow large enough to distort the ovary, or if the operation to remove them takes healthy ovarian tissue with it.
Cystadenomas. Benign growths arising from the outer surface of the ovary. They do not interfere with ovulation. As with dermoid cysts, the fertility question attaches to the surgery rather than to the cyst.
Paraovarian cysts. These sit next to the ovary rather than within it, in the tissue between the ovary and the fallopian tube. Because no ovarian tissue is involved, egg reserve is unaffected.
The cyst types that can affect fertility
Endometriomas. An endometrioma, often called a chocolate cyst, forms when endometriosis involves the ovary. This is the one cyst type with a well-established fertility link, and the link runs in two directions. The cyst occupies and replaces ovarian tissue, which can lower egg reserve. The underlying endometriosis causes inflammation and adhesions, bands of scar tissue that can alter the normal position of the ovary and tube. An endometrioma in both ovaries, or one in someone whose reserve is already low, changes the calculation considerably. Our guide to endometriosis and fertility covers the condition itself in full.
Large or persistent cysts. A cyst still present well beyond the window in which a functional cyst should have resolved is, by definition, not a functional cyst. Persistence is the signal that prompts review. What happens next depends on the features described on the repeat scan, not on a measurement alone. Size becomes relevant only when a cyst is large enough to affect the ovary mechanically or make egg collection difficult during fertility treatment.
Recurring cysts. Cysts that keep returning in the same ovary raise a different question: whether something is driving them. Repeated cycles of forming, being watched, and sometimes being operated on carry a cumulative cost to ovarian tissue that a single cyst does not. If you are planning a pregnancy, this pattern is worth raising explicitly rather than treating each episode as a fresh, isolated event.
How a cyst can interfere: the four mechanisms
A cyst being present and a cyst being the cause of difficulty conceiving are two different findings, and very little of what is written about ovarian cysts separates them. A cyst affects fertility only if it does one of four things.
Mechanism
What Happens
Which Cysts Do This
It Stops or Disrupts Ovulation
The cyst interferes with the normal growth and release of an egg, so cycles may become irregular or occur without ovulation.
Uncommon. Mainly very large cysts or cysts that produce hormones of their own.
It Distorts the Ovary or Surrounding Structures
Adhesions or anatomical distortion can move the ovary and fallopian tube out of their normal relationship, making it harder for a released egg to be picked up.
Endometriomas and cysts associated with previous pelvic surgery or infection.
The Underlying Condition Damages Egg Reserve
The disease causing the cyst, rather than the cyst itself, can reduce the pool of eggs available.
Endometriomas, particularly when both ovaries are affected.
It Physically Blocks Access During Egg Collection
During IVF, a cyst positioned in front of the ovary can make the follicles difficult to reach safely with the egg-collection needle.
Any sizeable cyst positioned between the needle path and the ovary.
This is the part that matters: a cyst doing none of these four things is not your fertility problem, and treating it will not change your chances. That is true regardless of what the report says about its size. If you are ovulating regularly, your follicle count and what it means for fertility is a far more useful conversation than the cyst itself.
It is also worth knowing the relationship can run the other way. Ovarian stimulation used during fertility treatment can itself produce cysts, which is a scheduling matter rather than a setback.
Does removing an ovarian cyst improve fertility?
No. Removing an ovarian cyst does not improve fertility on its own.
This is the single most useful thing to understand before agreeing to an operation, and it is not what most people are told. Surgery removes the cyst. It does not add anything to your egg reserve, your ovulation or your chance of conceiving. Where a cyst was not causing a problem in the first place, removing it changes nothing about your fertility.
It can also cost you something. An ovarian cystectomy, the operation that removes a cyst while preserving the ovary, works by finding the plane between the cyst wall and healthy ovarian tissue and peeling the cyst away. Some healthy ovarian tissue almost always comes with it. This is why AMH, the blood marker used as one indicator of egg reserve, commonly falls after the operation. The fall is largest after endometrioma surgery, and larger again where both ovaries are operated on.
This is not a fringe position. The 2022 ESHRE guideline on endometriosis states, as a strong recommendation, that surgery for an ovarian endometrioma should not be routinely performed before assisted reproduction in order to improve live birth rates, because the current evidence shows no benefit and surgery is likely to have a negative impact on ovarian reserve. The same guideline advises that specific caution be used to minimise ovarian damage whenever endometrioma surgery is carried out.
There is no medical alternative either. No medicine shrinks a cyst that has already formed. A Cochrane review of randomised trials found that combined oral contraceptives did not hasten the resolution of functional ovarian cysts in any trial included, whether those cysts arose spontaneously or after ovulation induction. This class of medication is used to reduce the chance of new functional cysts developing. It does nothing to one that is already there.
None of this means surgery is the right answer. It means surgery is a decision with a cost attached, weighed against symptoms, the type of cyst, your age, and your current reserve, rather than a routine box to be ticked before trying. If you have one ovary already, or have had ovarian surgery before, that cost is higher and the conversation should start earlier. Where a laparoscopy is being discussed, our guide to diagnostic laparoscopy before IVF sets out when it changes the plan and when it does not.
When a cyst is worth acting on before trying to conceive
There is no single rule, but there is a short list of situations where dealing with a cyst before trying is the reasonable call rather than the reflexive one.
Situation
Why It Changes the Decision
It Persists Beyond the Expected Resolution Window
A cyst that remains after two to three cycles is less likely to be a simple functional cyst, so its type and management may need reassessment.
The Report Describes Complex Features
Features described as complex should be assessed on their own merits, separately from any fertility considerations.
Symptoms Are Affecting Daily Life
Pain or pressure that interferes with normal activities may be a reason to consider treatment, particularly when symptoms are persistent or worsening.
A Confirmed Endometrioma Where Ovarian Reserve Is Already Low
This requires careful individualised decision-making because surgery may reduce ovarian reserve, while delaying treatment may also have fertility implications.
Egg Collection Is Planned and Access Is Obstructed
When a cyst lies between the needle and the follicles, it can create a practical problem during egg collection and may influence the treatment plan.
It Has Changed Noticeably Between Scans
A cyst that changes significantly on repeat imaging should be reviewed promptly, regardless of conception plans.
Two things change this calculation and are almost always left out. The first is age: time spent watching a cyst is time not spent trying, and that arithmetic is different at 38 than at 28. The second is how long you have already been trying. Size on its own is the weakest signal in this list, and a measurement in centimetres should never be the whole basis for an operation.
How much do these tests and procedures cost in India?
The figures below cover the investigations discussed on this page. They are indicative ranges supplied by Cloudnine Fertility centres rather than audited list prices, and they vary by city and by centre. Confirm current pricing with your centre before planning around any of them.
Test or Procedure
Indicative Range
When It Applies
Pelvic or Transvaginal Ultrasound
Rs 1,000 to Rs 3,500
The first-line investigation and, for most people, the only imaging needed.
AMH Blood Test
Rs 5,000 to Rs 6,500
Useful when ovarian reserve is relevant to the treatment decision.
Pelvic MRI, Where Indicated
Rs 12,000 to Rs 19,000
Considered when ultrasound does not provide enough information to characterise the cyst.
Tumour Marker Panel, Where Indicated
Rs 2,000 to Rs 5,000
Ordered according to the cyst's scan features and clinical context, rather than routinely.
Pre-Anaesthetic Assessment and Routine Pre-Operative Bloods
Rs 4,500 to Rs 8,000
Applies when an operation has been planned.
Histopathology of a Removed Cyst
Rs 1,500 to Rs 4,000
Typically performed after surgical removal to determine the nature of the cyst.
Antral Follicle Count, FSH and Oestradiol
Rs 5,000 to Rs 6,500
May be ordered as part of a wider ovarian-reserve or fertility assessment.
Laparoscopic Ovarian Cystectomy
Rs 75,000 to Rs 150,000
Only where assessment has established that surgery is appropriate.
What moves the total is the depth of the work-up, not the headline price of any single item. For most people, the entire cost is one consultation and one scan, because most cysts need nothing further. Costs rise when a scan raises a question that needs second-line imaging, when reserve testing is added because surgery is under consideration, or when an operation brings pre-anaesthetic assessment, theatre time and histopathology with it. Whether a procedure is done as day-care or requires an overnight admission is the single largest step change in the total. For the cost of fertility treatment itself, including IUI and IVF, see the dedicated treatment cost guide.
Ovarian cysts and IVF
A cyst seen on the baseline scan at the start of an IVF cycle is common, and it is usually a scheduling matter rather than a clinical one. That scan exists partly to confirm the ovaries are quiet before stimulation begins. A functional cyst found at that point may mean the cycle start is postponed for a few weeks while it resolves, or it may be drained so that stimulation can begin on schedule.
Aspiration, which means drawing the fluid out through a fine needle, is sometimes used for exactly this reason. It is a practical step to let the cycle proceed, not a treatment expected to improve the outcome.
The harder question is whether to operate on an endometrioma before starting IVF. The reserve trade-off described in the previous section applies directly, and current guidance is against doing it routinely to improve live birth rates. Where it is considered, the reasons are usually pain or straightforward physical access to the follicles at egg collection. If you are told a cyst will delay your cycle, useful questions include what type it is thought to be, whether the plan is to wait or drain it, and whether the decision changes your protocol. A delay of one cycle is not a signal that treatment will fail.
A cyst found during pregnancy
Finding a cyst on an early pregnancy scan is common and usually reassuring rather than worrying. Many of these are corpus luteum cysts, the structure left behind after the egg that became this pregnancy was released. It produces the hormone that supports the pregnancy through its earliest weeks and then shrinks away on its own, generally during the second trimester.
Other cysts found in pregnancy are usually monitored with repeat scans rather than treated. Most need nothing at all.
Surgery during pregnancy is uncommon and is reserved for specific situations, such as a cyst causing severe pain, one that has twisted or ruptured, or one whose appearance on imaging warrants assessment in its own right. Where it is needed, timing is planned carefully around the pregnancy. If a cyst has been mentioned on your scan, ask what type it appears to be and when the repeat scan is due. That is usually the whole of the plan.
One thing that is often confused
Polycystic ovaries are not ovarian cysts, despite the name. What a scan describes that way is a larger-than-usual number of small follicles sitting in the ovary, each an egg-containing sac that has not been released, rather than a collection of cysts. The distinction matters because the two findings are assessed and managed in completely different ways, and nothing on this page about cysts and conception should be read across to that appearance on a report.
Seek care immediately if
Some symptoms need in-person assessment today rather than a search result. Go to an emergency department or contact your treating clinician straight away if you have:
Sudden, severe pain low down on one side of the abdomen or pelvis
Pain together with fever or vomiting
Fainting, dizziness, or feeling as though you might pass out
Abdominal swelling that is increasing quickly
These can indicate that a cyst has twisted or ruptured, and both are time critical. Do not wait for a scheduled appointment.
What to ask at your consultation
These questions can change what happens next. Take them with you.
What type of cyst does the scan suggest, and how confident can we be from imaging alone?
Has it changed between scans, and when should the next scan be?
Is it doing any of the four things that actually affect fertility?
What is my egg reserve, and does that change the decision here?
If we operate, what specifically improves, and what might I lose?
What happens if we simply wait, and how long is reasonable given my age?
Should I be trying to conceive while we watch it?
If you leave with clear answers to those, you have what you need. Our guide to what to expect at your first fertility consultation covers how the appointment is structured and which tests usually come with it.
FAQs
Your questions, clearly answered
Find clear, trusted answers to the most common questions about IVF—designed to guide and support you every step of the way.
Do ovarian cysts affect fertility?
Most do not. The majority of ovarian cysts are functional cysts that form as part of normal ovulation and disappear on their own without affecting your chance of getting pregnant. The main exceptions are endometriomas and cysts that are large, persistent or recurring.
Can you get pregnant with an ovarian cyst?
Yes, in most cases. Having an ovarian cyst does not mean you are infertile. Many women conceive naturally with a cyst present and never know it was there.
Will removing an ovarian cyst improve my fertility?
Usually not. Removing a cyst does not improve fertility on its own, and surgery to remove a cyst takes some healthy ovarian tissue with it, which can lower your AMH and your egg reserve. Surgery is a decision with a cost, not a routine step before trying.
Is there a medicine that shrinks an ovarian cyst?
No. No medicine shrinks an ovarian cyst that has already formed. Some medication reduces the chance of new functional cysts developing, but it does nothing for an existing one.
How do I know if my ovarian cyst is the reason I have not conceived?
A cyst affects fertility only if it does one of four things: stops or disrupts ovulation, distorts the ovary or surrounding structures, damages your egg reserve through the condition causing it, or physically blocks access to the ovary during egg collection. If a cyst does none of these, it's unlikely to be the reason.
Does a cyst on my scan report mean something is wrong?
Often not. Ovarian cysts are one of the most common incidental findings on a pelvic scan. What matters is the type, whether it has changed between scans, and whether it is causing symptoms, not the fact that one was seen.
Do I need to treat an ovarian cyst before trying to conceive?
In most cases no. Treatment is considered when a cyst persists beyond the window in which it should have resolved, has complex features on the report, is causing symptoms that affect daily life, or is a confirmed endometrioma in someone whose egg reserve is already low.
Can an ovarian cyst delay IVF?
It can. A cyst seen on a baseline scan sometimes postpones the start of stimulation, and it may be monitored or drained before the cycle begins. This is a scheduling decision, not a sign that the cycle will fail.